An adult cough that continues beyond eight weeks needs a different assessment from a short-lived infection, especially when breathlessness, sputum, fever, weight loss or blood is present. You will learn when to book a pulmonology appointment, when to seek emergency care, what the first consultation involves, and how doctors choose between spirometry, imaging, sputum tests and bronchoscopy.
Key takeaways
- Seek assessment for an adult cough lasting over eight weeks.
- Children need evaluation when a cough lasts beyond four weeks.
- Report coughing blood, chest pain, severe breathlessness, or blue lips urgently.
- Bring symptom timing, triggers, medicines, smoking history, and previous test reports.
When a persistent cough or breathlessness needs medical attention
Book a pulmonologist for cough when it lasts beyond the expected recovery from an infection, keeps returning, or comes with chronic breathing difficulties. In an adult, a chronic cough lasting more than eight weeks needs assessment; children reach the commonly used chronic-cough threshold after four weeks.
Arrange an appointment sooner for wheezing, repeated chest infections, night sweats, unexplained weight loss, persistent fever, troublesome phlegm, or a smoking, vaping, dust, or chemical exposure.
Go to emergency care instead of waiting for a clinic appointment if you have:
- Severe or rapidly worsening breathlessness, especially at rest
- Blue or grey lips, confusion, collapse, or fainting
- Chest pain, particularly with sudden breathlessness
- A low measured oxygen saturation or a clear fall from your usual reading
- Coughing up more than a small streak of blood
These signs can indicate respiratory failure, a pulmonary embolism, severe infection, or another time-critical problem. Do not drive yourself if you are faint, confused, or struggling to breathe.
Tell the clinician about every medicine, including ACE inhibitors such as ramipril or lisinopril, because they can cause a dry cough weeks or months after treatment begins. Do not stop a prescribed medicine without advice; the prescriber can select a replacement.
A normal chest X-ray does not rule out asthma, early airway disease, or every lung condition, so persistent symptoms still deserve follow-up.
What a pulmonologist looks for in your symptoms and history
A cough lasting more than eight weeks in an adult is chronic, and its cause may be in the airways, nose, stomach, heart, medication history or an exposure. A pulmonologist looks for patterns rather than treating every persistent cough as infection.
| Cause | Clues the specialist looks for |
|---|---|
| Asthma | Night or exercise-related cough, wheeze, allergies, or cough-variant asthma without wheezing |
| COPD | Smoking or biomass-fuel exposure, daily phlegm and exertional breathlessness; confirmation requires post-bronchodilator spirometry |
| Post-infectious cough | Cough beginning after a cold, influenza or COVID-19 and gradually easing |
| Upper-airway cough syndrome | Throat clearing, nasal blockage, a dripping sensation or hoarseness |
| Gastro-oesophageal reflux cough | Heartburn, sour fluid, cough after meals or when lying down |
| Bronchiectasis or tuberculosis | Large sputum volumes, recurrent infections, fever, night sweats or weight loss |
| Medication, heart or lung disease | An ACE inhibitor, swelling, breathlessness when lying down, blood in sputum or unexplained weight loss |
More than one cause can coexist, so improvement after one treatment does not exclude another. Antibiotics do not treat asthma, reflux, medication-related cough or most viral illnesses.
Expect questions that ask you to describe:
- When the cough began and whether it is worsening
- A dry cough or sputum, including its colour and daily volume
- Wheezing, fever, night sweats, chest pain or breathlessness
- Blood, weight loss or symptoms that wake you at night
- Smoking, vaping, dust, fumes, mould, pets and workplace exposure
- Triggers such as exercise, cold air, meals, lying down or seasons
- Allergies, previous infections, medicines and relevant family history
What happens during the first pulmonology consultation
The first visit is a sorting exercise, not an automatic order for every scan. The pulmonologist records your breathing rate, performs an oxygen saturation measurement, listens for wheezing or crackles, checks your nose and throat, and examines your chest. Fever, swollen legs, rapid breathing, or visible breathing effort can change the urgency.
You will be asked about:
- How long the cough has lasted, whether it is dry or produces sputum, and whether wheezing, fever, night sweats, weight loss, blood, or chest pain occurs.
- Triggers such as exercise, cold air, allergens, workplace dust, and lying down.
- Smoking and vaping exposure, previous lung infections, tuberculosis contact, allergies, and earlier chest problems.
- Your medication review, including blood-pressure tablets. An ACE inhibitor cough can begin weeks or months after starting treatment; do not stop the medicine without the prescriber choosing a substitute.
The examination and history help determine the next step:
| Finding or review | What it can suggest | What it may prompt |
|---|---|---|
| Low oxygen saturation, confusion, or severe breathing effort | An urgent respiratory problem | Immediate emergency assessment rather than routine testing |
| Wheeze or reduced airflow | Asthma or chronic obstructive pulmonary disease | Spirometry, including post-bronchodilator measurements |
| Fever, focal crackles, or discoloured sputum | Infection or another active lung process | Chest radiograph and targeted laboratory or sputum testing |
| Normal examination with persistent symptoms | Asthma, reflux, medication-related cough, or early airway disease remains possible | Focused testing; a normal chest X-ray does not rule out every cause |
How doctors choose between spirometry, scans, sputum tests and bronchoscopy
Doctors match the test to the question, not simply to the length of your cough. A chest X-ray can show pneumonia, a mass, or major structural change, while a CT scan for bronchiectasis detects widened airways that a plain X-ray can miss.
| Test | What it can explain | When it applies |
|---|---|---|
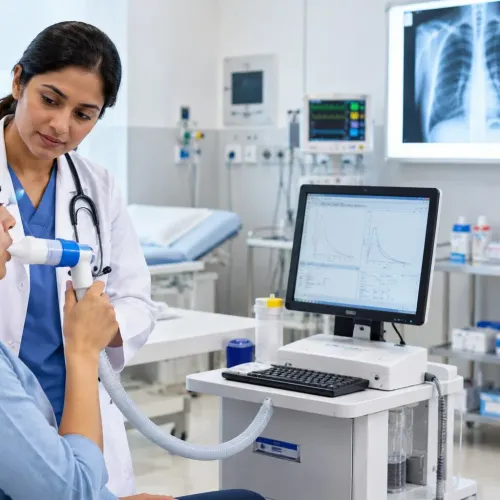
| Spirometry | Measures airflow and the FEV1/FVC ratio, helping confirm persistent obstruction; bronchodilator testing shows whether airflow improves after inhaled medicine | Suspected asthma or COPD |
| Sputum testing | Identifies bacteria, tuberculosis using rapid molecular testing, or abnormal cells | Phlegm, recurrent infections, blood in sputum, fever, night sweats, weight loss, or exposure risk |
| Chest X-ray | Shows pneumonia, fluid, collapse, or a visible mass | Common initial imaging test |
| CT scan | Provides detailed views of airways, lung tissue, blood vessels, and small lesions | Abnormal X-ray, unexplained symptoms, suspected bronchiectasis, cancer, or another focused indication |
| Bronchoscopy | Lets a specialist inspect the airways and collect washings, brushings, or biopsy samples | Abnormal imaging, unexplained bleeding, suspected airway blockage, or persistent cough after non-invasive tests |
During spirometry, you wear a nose clip, seal your lips around a mouthpiece, inhale fully, then blow out as hard and long as possible. The manoeuvre is repeated for reliable readings, then repeated after a bronchodilator when indicated.
A post-bronchodilator FEV1/FVC ratio below 0.70 supports COPD; cough alone or an abnormal X-ray does not establish it.
Bronchoscopy is not an automatic next step for persistent cough. Doctors justify it when scans or sputum results point to a problem that requires direct sampling, or when serious disease remains unexplained. Discuss bronchoscopy sedation preparation risks, including fasting, medication changes, bleeding, infection, and temporary breathing problems, before consenting.
How specialist care guides treatment and follow-up
A pulmonologist matches treatment to the cause, not simply to cough severity. The plan considers examination findings, imaging, spirometry, sputum results, medicines, smoking or workplace exposure, and your response over time. Routine antibiotics are not appropriate unless testing supports a bacterial infection or another defined indication.
When the findings point to a specific problem, the next step may be:
- Tuberculosis evaluation with chest imaging and rapid molecular testing of a respiratory specimen, followed by the correct treatment if confirmed. Do not replace this assessment with repeated antibiotic courses.
- Bronchiectasis care, which can include airway-clearance techniques, sputum-guided antibiotics for flare-ups, vaccination, and monitoring for recurring infections.
- Lung cancer assessment when a scan shows a suspicious nodule or mass. Doctors may need tissue diagnosis, staging, lung-function testing, fitness assessment, and biomarker results before choosing treatment.
Follow-up checks whether breathlessness, sputum, wheeze, sleep, and exercise tolerance are improving. The doctor may correct inhaler technique, adjust doses, repeat spirometry, review oxygen readings, or investigate a new warning sign rather than continuing an ineffective treatment.
A thoracic surgeon referral is useful for selected lung cancers, mediastinal masses, pleural disease, or severe structural damage. It does not confirm cancer or guarantee an operation.
Galaxy Chest & Multi Specialty Hospital Pvt Ltd can be relevant when pulmonology, thoracic surgery, investigations, and hospital-based respiratory care need coordination, especially if oxygen levels fall or the condition becomes unstable.
Frequently asked questions
When does a persistent cough need a pulmonologist?
An adult cough lasting more than eight weeks needs assessment. Children reach the commonly used chronic-cough threshold after four weeks. Arrange earlier care when the cough keeps returning or accompanies ongoing breathing difficulty.
What does a pulmonologist ask about chronic cough and breathlessness?
The doctor reviews when symptoms began, their pattern, triggers, phlegm or blood, wheezing, fever, chest pain, night symptoms, smoking or workplace exposure, medicines, allergies, past illnesses, and previous test results.
What happens during a first pulmonology consultation?
The consultation includes a symptom and medical-history review, examination of breathing and chest sounds, and a decision about tests. Bring medication details, prior reports, and a record of symptom timing.
How do doctors choose between spirometry, scans, sputum tests, and bronchoscopy?
Spirometry measures airflow for conditions such as asthma or chronic obstructive pulmonary disease. Chest X-rays or CT scans examine lung structure. Sputum tests analyse mucus for infection or other causes. Bronchoscopy lets a specialist inspect the airways and collect samples when less invasive tests do not answer the clinical question.